
Health
“Everybody has heard how it kills”: Uganda’s veteran health system ramps up its Ebola response


Dr Diana Atwine had just sat down at her desk in Uganda’s Ministry of Health on 19 September when she received a phone call. Blood samples her office had sent to the country’s virus research institute in Entebbe were positive for a rare type of Ebola, the so-called Sudan strain.
A jolt of fear ran through Dr Atwine.
Having served as the Ministry’s Permanent Secretary – its most senior non-political figure – since 2016, Dr Atwine was well aware of Uganda’s impressive record in handling outbreaks of the viral haemorrhagic fever.
Most recently in 2019, a family infected with the ‘Zaire’ strain of Ebola had travelled to Uganda from epidemic-hit DRC. Uganda’s response had been quick and competent: by isolating the cases and their contacts, and ring-vaccinating to contain potential spread, in-country transmission was snuffed out before it had a chance to get going.
But she also knew that this time, they were down one crucial tool: the Sudan ebolavirus currently has no available vaccine. Dr Atwine grabbed a notebook and began making phone calls.
The same day, a rapid response team was dispatched by her ministry to collect information and personal details from suspected cases – people who might have come in contact with patient zero, a young man from Mubende district, about 135km west of the capital, Kampala.
The team was also tasked with setting up Ebola isolation and treatment units in the area, isolating exposed individuals and monitoring them for symptoms.
But the virus had already spread.
Verbal autopsies indicated that six people from the Mubende man’s family – three adults and three children – had died of the virus between 11 and 15 September in the two sub-counties of Madudu and Kiruma.
As of 26 October, more than 109 people in Uganda have contracted the virus while 30 have died. The virus has also been confirmed in five districts in Uganda, including, alarmingly, in the busy, well-connected capital.
“We have to be very effective to stop this virus,” Dr Atwine told VaccinesWork.
Community-level containment
The rapid spread of the deadly virus has worried local leaders and a community that is still struggling to recover from the effects of COVID-19.
“We are afraid of the disease. Everybody has heard how it kills,” says Justus Mucunguzi, a trader in Kampala. “But we are also afraid government might impose another lockdown in Kampala (if cases continue to rise), when people don’t have food to eat.” Government has already imposed limited lockdowns in Mubende and Kassanda districts, the two epicentres.

Credit: Emmanuel Ainebyoona, Ugandan Ministry of Health
The outbreak response – rapid case detection, isolation of contacts, and treatment for the sick – has been aggressive, and the pace is only ramping up. Working with the African Centres for Disease Control and Prevention (Africa CDC) and the World Health Organization, Uganda’s Ministry of Health is training teams in contact tracing, health workers in case management, and laboratory scientists in improving surveillance.
It is also training teams to bury the dead safely, is educating communities and mobilising volunteers, especially people who have previously worked on Ebola case management.
“The biggest challenge was that the community (in Madudu and Kiruma sub-counties) delayed in reporting cases to health facilities when people started to show Ebola-like symptoms,” says Dr Daniel Kyabayinze, Director of Public Health at the Ministry of Health. “Instead of coming to health facilities, they attributed the illnesses to witchcraft.”
At the Ebola isolation and treatment centres set up by the Ministry at the Mubende Regional Referral Hospital and in Kassanda and Entebbe districts, exposed individuals are isolated, tested and then watched for a period of 21 days – the virus’s incubation period. As of 25 October, the teams were monitoring more than 1,800 people.

Credit: Emmanuel Ainebyoona, Ugandan Ministry of Health
Those who develop symptoms and test positive for the virus are contained in separate units, and started on supportive treatment. Dr Kyabayinze says that the US has provided Gilead Sciences’ remdesivir and Mapp Biopharmaceutical Inc’s trial Ebola antibody drug to help control the virus.
Mubende and Kassanda districts, meanwhile, remain under dusk-to-dawn lockdown. Speaking at a press briefing, Dr Ahmed Ogwell, acting director of Africa CDC, said that the lockdowns are time limited for 21 days so that “we can contain spread (of the virus). After the 21 days the situation can be assessed again.
“It is not one of those tools that we like, but it is necessary if a threshold has been reached,” he added.
Adding to the arsenal
The Ministry of Health is working with neighbouring countries, including Rwanda, Kenya and the Democratic Republic of the Congo, to step up surveillance of the virus. It is also working with the WHO to test candidate vaccines for the Sudan Ebolavirus. The most promising is a single-dose ChAd3 Ebola Sudan Vaccine being developed by the Sabin Vaccine Institute in the US.
Emmanuel Ainebyoona, senior public relations officer at the health ministry, says that they are ready to start the vaccine trials as soon as they receive the doses.
“We are doing all we can to stop the virus,” said Dr Kyabayinze. “We are urging the communities to follow the processes we have shared, especially in terms of isolating when they develop symptoms. If they trust in the doctors, we shall contain this virus.”
gavi.org





The recent flag-off of 116 ambulance vehicles by the Ministry of Health signifies not just an augmentation of emergency medical resources but a remarkable shift in Uganda’s healthcare landscape. This initiative, led by Dr. Diana Atwine, the Permanent Secretary, highlights a concerted effort to transform the country’s emergency response system, evolving from basic transport vans to equipped, life-saving ambulances.
Dr. Atwine’s announcement regarding the transition is significant. By 2016, Uganda possessed 173 Type A Road Ambulance Vehicles, serving merely as patient transport vans with minimal emergency care capabilities. However, the country has now surged ahead, boasting 187 Type B Road Ambulance Vehicles equipped with Basic Life Support tools, 4 Type C Road Ambulance Vehicles with Advanced Life Support equipment, 11 Type B Boat Ambulances, and 3 Type C Boat Ambulances. This stark evolution underlines the government’s commitment to phasing out outdated ambulance models and replacing them with advanced, fully-equipped vehicles.

The shift is a testament to Uganda’s dedication to enhancing emergency medical services. The shift from basic vehicles without standard equipment to advanced ambulances equipped with life-saving tools signifies a conscious effort to prioritize the well-being of citizens during emergencies. It’s a leap from mere transportation to providing critical care on the move.
Dr. Atwine’s vision, aiming for a fully operational National Ambulance Service by FY 2025/26, reflects the government’s forward-looking approach. The significance of this milestone extends beyond the numbers; it represents a comprehensive strategy to address emergency medical needs, aligning with global standards of care and response.
The inclusion of boats as ambulance vehicles also underscores a holistic approach to addressing emergencies, particularly in regions accessible only by waterways. This diversification of resources demonstrates a nuanced understanding of Uganda’s geographic diversity and a commitment to ensuring emergency care reaches even the most remote areas.
As Uganda moves towards this new era in emergency medical services, the focus remains on efficient utilization and adherence to stringent guidelines for ambulance usage. Dr. Atwine’s emphasis on proper management and utilization, including trained personnel and approved protocols for ambulance dispatch, signifies a holistic approach to maximizing the impact of these life-saving resources.
The shift from basic transport to advanced care within the ambulance fleet is not just a numerical upgrade; it’s a paradigm shift towards ensuring that every Ugandan, regardless of location or circumstance, has access to critical and timely medical care during emergencies.

Uganda is making strides in the sector as it seeks to provide quality services to the citizenry. As part of efforts to achieve this, the government through the Ministry of Health has established three state-of-the-art Specialized Reference Laboratories under National Health Laboratory and Diagnostic Services (NHLDS).

They are; The Central Public Health Laboratories (CPHL), the National Tuberculosis Reference Laboratory (NTRL) and National Microbiology Reference Laboratory (NMRL), all of which are accredited to International Standards, meaning that their results are trusted anywhere in the world.

These reference Laboratories are supplemented by the Lab capacities in research institutes such as the Uganda Virus Research Institute (UVRI) Laboratory, Joint Clinical Research Centre (JCRC) and universities (Makerere, Mbarara, Gulu, etc) whenever need arises.
Major Capacities in the Reference Laboratories
The major Capacities of the National Health Laboratory Services are as follows: –
✓ Capacity to test for COVID-19 in Butabika, and with mobile Laboratories currently placed in Tororo, Adjumani Hospital (for Elegu border crossing), Mutukula and Mubende Regional Referral Hospital. Additionally, all the Regional Referral Hospitals have been equipped with GeneXpert machines which the department activates any time additional testing capacity is needed. These Laboratory has been the cornerstone in the Ministry’s strong response in the prevention, management and control of the ongoing COVID-19 by providing quality and real-time results for decision-making.

✓ Capacity of National TB Reference Laboratory (NTRL) to consistently provide surveillance and early detection of Multidrug Resistant Tuberculosis (MDR-TB) and Extremely Resistant TB (XDR-TB) to help in early detection and isolation of cases to prevent spread and protect life.
✓ Capacity to provide testing for diagnosis of HIV and Hepatitis B including Viral Load for up to 2.5 million tests every year thereby providing access door to life saving ARVs and treatment monitoring for people living with HIV/AIDS and Hepatitis B including babies and pregnant mothers.
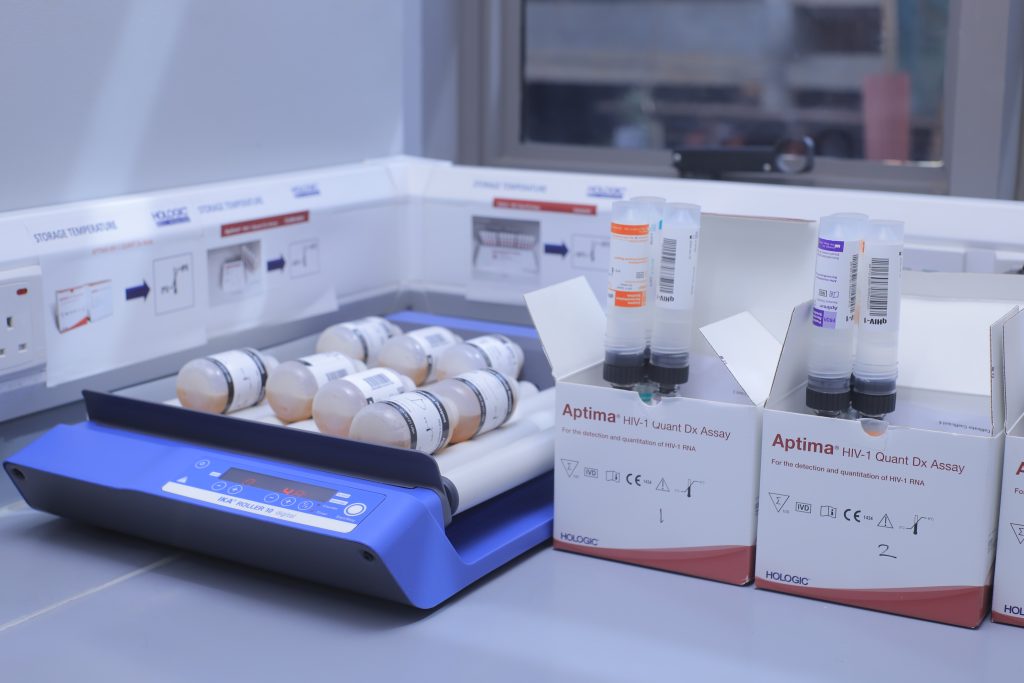
✓ Capacity for sickle cell disease confirmation, Heme Path Cancer Diagnosis and other non-communicable and lifestyle disease diagnosis.
✓ Capacity for routine diagnostic check-ups for functions of the Kidney, Liver, Heart and other vital organs of the body.

✓ Established the genomic Laboratories at the Central Public Health Laboratory (CPHL) and National Tuberculosis Reference Laboratory (NTRL) for routine surveillance of any genetic changes in disease–causing microorganisms that may result in being very dangerous (like resistance to treatments) or weaker and therefore milder.
✓ Capacity of the National Microbiology Reference Laboratory to carry out routine bacterial culture and sensitivity for Antimicrobial Resistance (AMR) surveillance.

✓ Developed laboratory information management systems which is used at the in the refence Laboratories (CPHL and NTRL) to track patients’ samples and relay results to the Doctors. For example, the TB Lab information system tracks patient samples and rely results to MDR treatment sites in the country, which has greatly improved turn round time for TB culture and drug susceptibility results.
✓ The External Quality Assessment (EQA) Laboratory. The reference Laboratories at NHLDS produce Proficiency testing panels that are accredited to ISO Standards which are used to expertly control the quality of Laboratory diagnosis across the national health laboratory network.

✓ Equipment Calibration Centre. The NHLDS has an internationally accredited equipment calibration Centre that supports calibration and standardization of equipment in the whole Laboratory sub-sector in the country to ensure they provide accurate results.
✓ The Laboratory Department (through NTRL and CPHL) Supports 26 countries in Africa as part of the World Health Organization – given mandate, and has supported ISO 15189 accreditation of 11 National Reference laboratories in the region. This is marketing Uganda’s healthcare system internationally.

















Ther Ministry of Health PS, Dr Diana Atwine, on Tuesday, commissioned the newly refurbished maternity ward at Butenga HC IV in Bukomansimbi District.
It was refurbished with support from Korean Foundation for International Health (KOFIH).

Additionally, KOFIH also supported the construction and equipping of the Surgical Ward, OPD and Emergency Unit Block.

Digital X-rays, ambulance and emergency care equipment and supplies have been procured to support health service delivery at Bukomansimbi District.
“Once we have buildings, equipment and health workers, patients will come and receive quality services,” Dr Atwine said during the ceremony.
She added, “All this capacity is enabling Butenga HCIV to handle referrals from Bukomansimbi, Masaka, Lwengo, Ssembabule and Kalungu and from as far as Gomba.”
https://x.com/DianaAtwine/status/1701522964896776336?s=20


-
 News11 months ago
FACTS ABOUT WORSHIP HARVEST: History, Growth, and Vision
-
 News11 months ago
EU Envoy Sadek Visits Phaneroo, Commends the Ministry’s Impact on Ugandan Youth
-
 Environment4 years ago
What Can Christians Do About Climate Change?
-
News2 years ago
US Televangelist Benny Hinn reveals his ‘2 biggest regrets;’ Preaching Prosperity Gospel, False Prophecies
-
 News11 months ago
Vote for Continuity of Peace and Stability, First Lady Janet Museveni Urges Ugandans